Under the IWGDF 2023 guideline, people with diabetes are sorted into four foot-risk categories. Category 0 (no sensation loss and no artery disease) needs a foot exam once a year; category 1 every 6 to 12 months; category 2 every 3 to 6 months; category 3, after an ulcer, amputation or on dialysis, every 1 to 3 months.
These diabetic foot check guidelines are designed to identify people who need closer surveillance before another wound develops. Your screening frequency is not decided by diabetes alone. Loss of protective sensation, peripheral artery disease (PAD), foot deformity, previous ulcer, amputation and end-stage kidney disease can all change your risk category.
At Elegance Diabetic Foot & Ulcer Clinic (EDFC), risk-based assessment can be used to document a patient's current category and guide follow-up. Screening performed by trained staff can be reviewed by Dr. Ashutosh Shah, with the risk category recorded for future comparison.
What Decides Your IWGDF Foot Risk Category?
The diabetic foot risk classification is based on specific findings rather than how healthy your feet appear.
A foot can look completely normal while sensation or circulation is already impaired. This is one reason preventive screening is important.
The assessment particularly looks for:
-
Loss of protective sensation
-
Peripheral artery disease
-
Foot deformity
-
Previous diabetic foot ulcer
-
Previous lower-limb amputation
-
End-stage kidney disease
A Diabetic foot screening assessment helps identify these risk factors before deciding how frequently the feet should be reassessed.
IWGDF Category 0: Very Low Risk
Category 0 means there is no loss of protective sensation and no peripheral artery disease.
This does not mean that foot care can be ignored. Diabetes-related nerve or vascular changes may develop over time, so screening should continue.
Recommended screening frequency: once every year.
IWGDF Category 1: Low Risk
Category 1 applies when loss of protective sensation or peripheral artery disease is present.
Once sensation or circulation is impaired, a small injury may become more important because pain may not provide an early warning or tissue may have a reduced ability to tolerate injury.
Recommended screening frequency: once every 6–12 months.
IWGDF Category 2: Moderate Risk
Category 2 involves a combination of risk factors. This can include loss of protective sensation with PAD, loss of protective sensation with a foot deformity, or PAD with a foot deformity.
Because several risk factors are interacting, examination needs to become more frequent.
Recommended screening frequency: once every 3–6 months.
IWGDF Category 3: High Risk
Category 3 is the highest IWGDF risk group.
It includes people with loss of protective sensation or PAD who also have a history of:
-
Foot ulcer
-
Lower-extremity amputation
-
End-stage kidney disease
A healed ulcer therefore does not automatically return someone to the lowest-risk category.
Recommended screening frequency: once every 1–3 months.
Patients in this group may benefit from structured follow-up through a High-risk foot programme.
How Often Should Each Category Be Screened?
One of the most useful parts of the diabetic foot check guidelines is that they give risk-based screening intervals rather than recommending the same schedule for every person with diabetes.
IWGDF Diabetic Foot Risk Table
| IWGDF category | Main criteria | Screening interval | Footwear and education |
|---|---|---|---|
| 0 – Very low | No loss of protective sensation and no PAD | Once yearly | Basic preventive foot-care education and appropriate footwear |
| 1 – Low | Loss of protective sensation or PAD | Every 6–12 months | Reinforced foot-care education and attention to footwear |
| 2 – Moderate | Loss of protective sensation + PAD; loss of protective sensation + deformity; or PAD + deformity | Every 3–6 months | Closer footwear assessment, preventive education and regular review |
| 3 – High | Loss of protective sensation or PAD plus previous ulcer, amputation or end-stage kidney disease | Every 1–3 months | Intensive preventive care, appropriate footwear and frequent professional review |
This diabetic foot check up frequency means a person with no identified neuropathy or PAD may only need formal risk screening annually, while someone with a healed ulcer may require reassessment every few months.
The interval should not be treated as a reason to wait if a new problem appears. A blister, cut, redness, swelling, discharge, colour change or new foot pain should be assessed when it occurs.
Which Tests Make Up a Proper Screening Exam?
A diabetic foot screening should be more than simply looking at the skin.
The examination should assess several areas that influence ulcer risk.
1. Medical and Foot History
The examiner should ask about previous:
-
Foot ulcers
-
Amputations
-
Foot infections
-
Vascular disease
-
Kidney disease
-
Neuropathy symptoms
-
Previous foot procedures
A previous ulcer is particularly important because a healed wound still influences future risk classification.
2. Skin and Nail Examination
The feet should be inspected for:
-
Callus
-
Cracks
-
Blisters
-
Nail problems
-
Pressure marks
-
Colour changes
-
Swelling
-
Skin damage
-
Existing wounds
Areas between the toes should also be examined.
3. Foot Shape and Deformity
Prominent bones, altered toe positions and other deformities may create concentrated pressure inside footwear.
When sensation is reduced, repeated pressure may occur without enough pain to warn the patient.
4. Circulation Assessment
The examiner assesses for signs suggesting peripheral artery disease.
Depending on the findings, further vascular testing may be needed. Reduced circulation matters because it can increase ulcer risk and make wound healing more difficult.
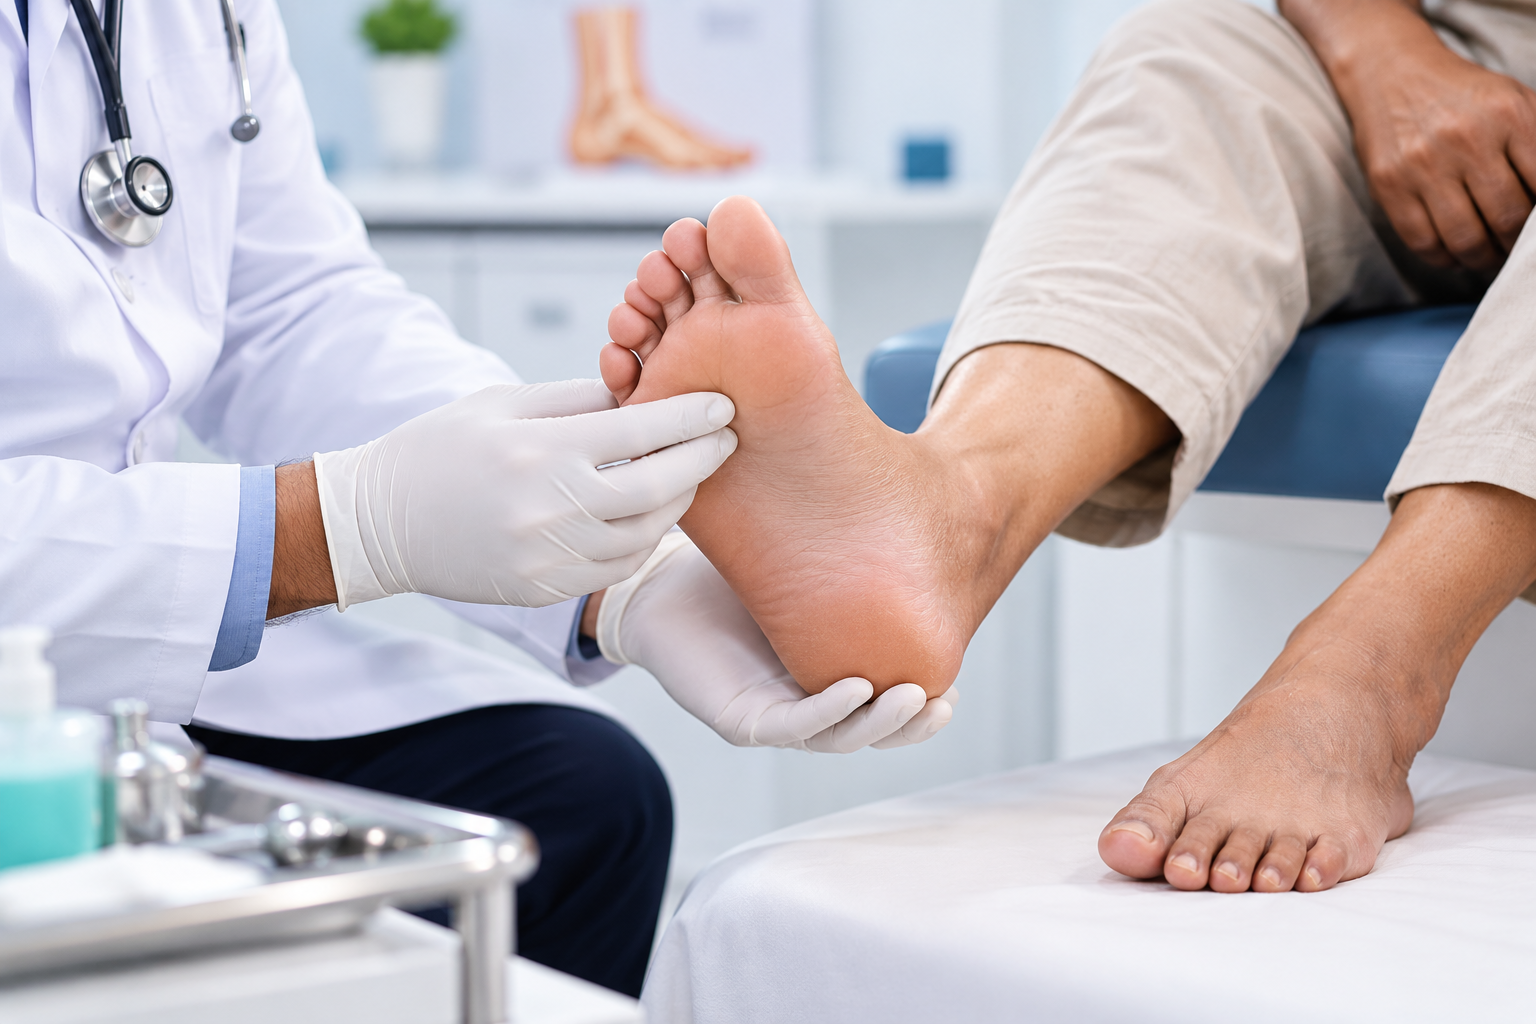
5. Diabetic Foot Check Monofilament Test
The diabetic foot check monofilament assessment uses a 10 g monofilament to test protective sensation at selected areas of the foot.
The filament is applied with enough pressure to bend it. The patient indicates whether the pressure can be felt.
The test is painless and usually takes only a short time.
Loss of protective sensation matters because someone may not notice:
-
A stone inside a shoe
-
A blister
-
Excessive pressure
-
A minor cut
-
Heat injury
-
Repetitive friction
A person can therefore develop tissue damage without experiencing the level of pain normally expected from the injury.
For patients who need a broader assessment of sensation, circulation, skin, deformity and previous foot problems, a Comprehensive foot evaluation can help establish the overall risk profile.
What Is IWGDF Risk Stratification?
IWGDF risk stratification turns findings from the foot examination into an actionable follow-up schedule.
The purpose is not simply to give the patient a category number. The category helps determine how closely the feet should be monitored and what preventive measures deserve greater attention.
For example, two people may both have diabetes for ten years. One may have intact protective sensation, no PAD and no previous ulcer. The other may have neuropathy and a previously healed ulcer.
Their preventive requirements are therefore different even though both have diabetes.
Risk stratification helps distinguish those situations.
Can Your IWGDF Category Ever Go Down?
Risk categories should be reassessed rather than assumed to remain unchanged forever.
Some findings can change. Circulation may change, deformity may progress, or loss of protective sensation may be identified during a later examination.
However, historical factors remain important.
In particular, a previous diabetic foot ulcer or amputation continues to matter even after the immediate problem has healed.
A person should therefore not assume:
"My ulcer healed, so I am back to normal risk."
Healing the ulcer is a major achievement, but preventing recurrence becomes the next priority.
What Changes in Care When You Move Up a Category?
Moving into a higher-risk category generally means the preventive strategy becomes more intensive.
Changes may include:
-
More frequent professional foot examinations
-
More attention to footwear
-
Regular skin inspection
-
Callus management where appropriate
-
Patient and family education
-
Earlier assessment of new lesions
-
Closer monitoring of circulation
-
Pressure-relieving strategies when indicated
Patients at higher risk should also inspect their feet regularly at home.
Look at the soles, heels, sides of the feet and between the toes. If you cannot see the sole easily, a mirror or help from a family member may be useful.
The objective is to identify a problem while it is still small.
Diabetic Foot Screening in Vizianagaram: Why Risk Category Matters
For people seeking diabetic foot screening in Vizianagaram, the useful question is not only whether a foot examination has been performed, but whether the findings have been translated into a recognised risk category and follow-up interval.
A screening assessment should help answer:
-
Is protective sensation intact?
-
Is PAD suspected or present?
-
Is there a significant foot deformity?
-
Has there been a previous ulcer?
-
Has there been an amputation?
-
Is end-stage kidney disease present?
-
When should the next examination occur?
Recording the category also makes future reviews more meaningful because clinicians can see whether the patient's risk profile has changed.
Screening Is Preventive Care, Not Just Wound Care
Many people first think about a diabetic foot specialist after a wound appears.
The purpose of diabetic foot check guidelines, however, is partly to identify risk before ulceration occurs.
Someone without an ulcer may still have neuropathy, PAD, deformity or pressure points that increase future risk.
Preventive screening creates an opportunity to address footwear, daily inspection, skin care and other modifiable problems before they contribute to tissue breakdown.
Community Screening camps can also help identify people who may need more detailed evaluation or ongoing surveillance.
When Should You Get Checked Earlier Than Your Scheduled Visit?
The IWGDF screening interval is intended for routine preventive follow-up. It should not delay assessment of a new problem.
Seek medical evaluation sooner if you notice:
-
A new blister
-
A cut that is not improving
-
Redness or warmth
-
New swelling
-
Fluid or discharge
-
A new pressure mark
-
Black or unusually pale skin
-
A new crack or ulcer
-
Sudden changes in foot shape
-
New pain or unexplained discomfort
People with neuropathy should be especially careful because serious problems may sometimes produce surprisingly little pain.
Conclusion
The main purpose of the diabetic foot check guidelines is to match the frequency of preventive examinations to the person's actual risk. Someone in category 0 does not need the same surveillance schedule as someone with neuropathy, PAD or a history of ulceration.
Knowing your IWGDF category gives you a practical answer to an important question: when should my feet be examined again?
At Elegance Diabetic Foot & Ulcer Clinic (EDFC), trained staff can perform structured foot-risk screening, with findings reviewed by Dr. Ashutosh Shah when appropriate. Recording the risk category can also make subsequent reviews more consistent and help patients understand the preventive care their feet require.
quiz Frequently Asked Questions
This article is general education, not a diagnosis. If you have a diabetic foot wound, please have it assessed in person. Send a photo on WhatsApp or book a consultation.
About the Author

Dr. Ashutosh Shah, Plastic, Reconstructive & Diabetic Foot Surgeon, Elegance Diabetic Foot & Ulcer Clinic, Surat
Dr. Ashutosh Shah is a board certified plastic and reconstructive surgeon with over 22 years of experience and more than 10,000 limbs and feet saved. He founded Elegance Diabetic Foot & Ulcer Clinic, India's first chain of clinics dedicated to foot care, with centres in Surat and OPD partners across South Gujarat. He is known for a limb first approach, safe wound care and ethical, natural results.